
Signs You Need Hyaluronic Acid Injections for Knee Pain in Charlotte
Published July 4, 2026 | Last reviewed: July 14, 2026 | Category: Treatments & Services | Location: Charlotte, North Carolina
🕒 12 MINUTOS DE LEER
That grinding sensation when you climb stairs. The stiffness that makes it hard to rise from a chair. The dull ache that interrupts your sleep. If your knee consistently feels like machinery that’s lost its lubrication, you may be experiencing the effects of declining hyaluronic acid — a naturally occurring molecule that gives healthy synovial fluid its viscous, cushioning, and lubricating properties.
As osteoarthritis develops, the concentration and quality of hyaluronic acid in the joint falls. The synovial fluid becomes thinner and less protective, friction increases between cartilage surfaces, and the classic symptoms of knee OA follow. Inyecciones de ácido hialurónico — also called viscosupplementation — are FDA-approved for knee osteoarthritis and aim to restore some of that lost joint lubrication directly.
This article explains what hyaluronic acid does in the knee, the five signs that may indicate you are a candidate for injections, what the current evidence shows, and what to expect at Joint Health Solutions in Charlotte.
What Is Hyaluronic Acid and How Does It Help Your Knees?
Hyaluronic acid is a large glycosaminoglycan molecule found naturally in connective tissues, skin, and joint fluid. In the knee, it is the key component responsible for the viscoelastic properties of synovial fluid — the thick, slippery liquid that coats the cartilage surfaces and allows them to glide against each other with minimal friction.
In a healthy joint, synovial fluid with adequate hyaluronic acid acts simultaneously as a lubricant during rapid movements and as a shock absorber during slow, high-load movements. It also has a role in nourishing the avascular cartilage and modulating local inflammatory responses.
Osteoarthritis disrupts this system in two ways. First, cartilage gradually breaks down and loses thickness. Second, the synovial fluid itself changes — hyaluronic acid concentration drops, its average molecular weight decreases, and the fluid loses its normal viscoelastic behavior. The result is increased friction, greater vulnerability to impact stress, and a joint environment that is less hospitable to healing.
Hyaluronic acid injections introduce a sterile, gel-like preparation of exogenous hyaluronic acid directly into the joint space to supplement what the body is no longer producing adequately. For appropriate patients, this can reduce pain and improve function — though the magnitude of benefit varies, and not all patients respond.
5 Signs Your Knee May Need Hyaluronic Acid Injections
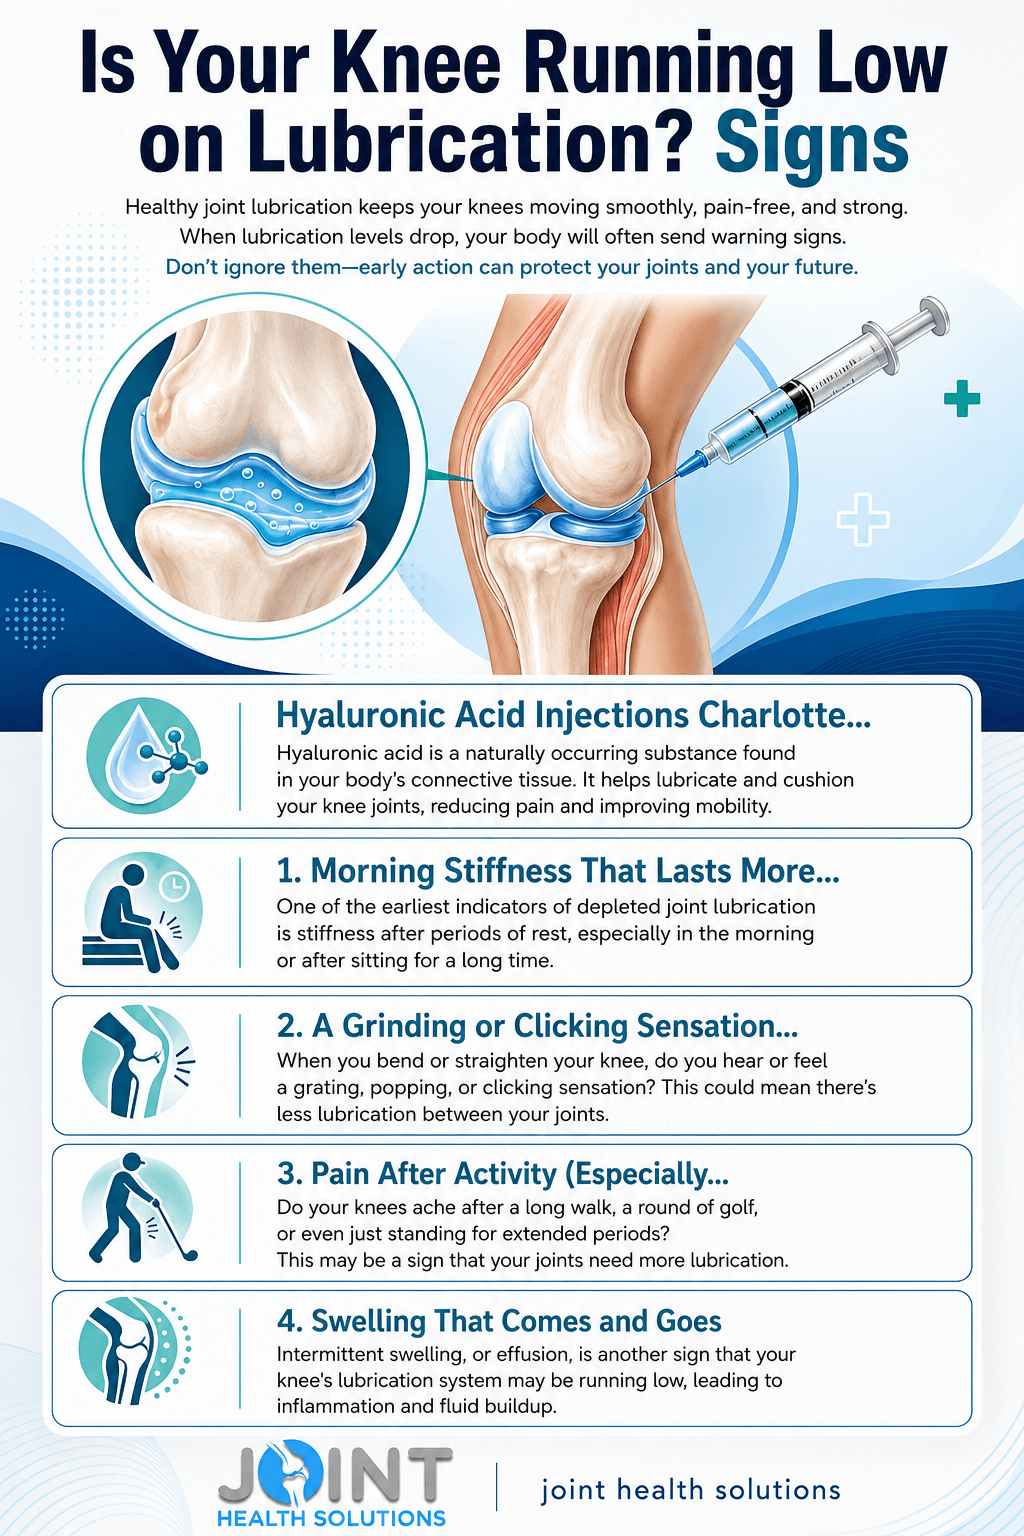
1. Morning Stiffness Lasting More Than 30 Minutes
One of the earliest indicators of advancing knee OA is stiffness after periods of inactivity, especially on waking. Healthy joints warm up quickly; a joint with diminished synovial fluid quality remains resistant to movement longer. If you consistently need 30 minutes or more before your knee loosens enough to walk normally — and this is not improving with exercise and conservative care — it may be time to discuss whether you are a candidate for viscosupplementation.
2. Grinding or Clicking Sensation (Crepitus)
A grating, popping, or clicking sensation when bending or straightening the knee — called crepitus — often indicates that cartilage surfaces are no longer gliding smoothly. In a well-lubricated joint, the viscoelastic synovial fluid keeps surfaces separated and moving silently. As lubrication declines and cartilage thins, these surfaces come into closer contact and the friction generates audible and palpable sensations. Occasional painless clicking can be normal; persistent grinding accompanied by pain or stiffness is more significant and worth evaluating.
3. Pain After Activity, Especially Weight-Bearing
Pain that consistently worsens with walking, standing, climbing stairs, or other weight-bearing activity — and eases with rest — is a classic pattern of knee OA. As cartilage thins and joint lubrication declines, the cartilage becomes less capable of absorbing repetitive mechanical load, leading to pain and micro-damage that accumulates with activity. When this pattern is no longer adequately controlled by physical therapy, weight modification, or oral analgesics, injection therapy becomes a reasonable next step to evaluate.
4. Intermittent Swelling Around the Knee
Fluctuating effusion — the knee appearing mildly puffy or feeling tight, especially after activity — is a common feature of knee OA. When the joint is under stress and the protective properties of synovial fluid are diminished, the body produces excess inflammatory fluid as a response. This is distinct from the acute, significant swelling following an injury. If you notice your knee regularly swelling after activity or feeling warmer than the other knee, this pattern warrants clinical evaluation.
5. Declining Function with Daily Activities
When knee OA progresses, functional limitations become increasingly apparent: avoiding stairs, using handrails consistently, needing to push off with your arms to stand, or abandoning activities you previously enjoyed. These limitations are a meaningful signal that your current management strategy is not adequately controlling your symptoms. The goal of hyaluronic acid injections is to reduce pain sufficiently to allow better participation in daily activities and physical therapy — not to eliminate the underlying OA.
¿Quién es un buen candidato?
Not every patient with knee pain is appropriate for viscosupplementation. The best outcomes are typically seen in:
- Adults with mild to moderate knee osteoarthritis confirmed on imaging (X-ray showing joint space narrowing consistent with OA grade I–III)
- Persistent symptoms that interfere meaningfully with daily function
- Inadequate relief from first-line conservative treatments: structured physical therapy, weight management, NSAIDs or acetaminophen, activity modification
- No active joint infection or skin breakdown near the injection site
- No known allergy to hyaluronic acid products
- Note: some HA products are derived from avian sources (rooster comb); patients with known poultry allergies should inform their provider so an appropriate product can be selected
Patients with end-stage OA (grade IV, bone-on-bone) tend to respond less well; surgical evaluation may be the more appropriate next step for this group. Patients with inflammatory arthritis (rheumatoid arthritis, gout) may obtain symptomatic benefit from HA injections but require separate management of the underlying systemic disease.
At Joint Health Solutions, we conduct a thorough evaluation — including medical history, physical examination, and imaging review — before recommending any injection therapy. We also discuss alternatives including cortisone injections, Terapia con PRP, y Descarregar los tirantes de rodilla.
What to Expect During and After Your Injection
The procedure is performed in our office. After cleaning the skin over the knee, the clinician may apply a numbing agent. Using a thin needle placed into the joint space, the hyaluronic acid gel is injected directly into the knee. You may feel mild pressure; most patients tolerate the procedure well. Depending on the product used, you may receive a single injection or a series of 1 to 3 injections spaced approximately one week apart.
After the injection, you go home the same day. Mild soreness, warmth, or swelling at the injection site is common and typically resolves within 48 to 72 hours. We recommend avoiding strenuous activity and prolonged weight-bearing on the knee for 48 hours. Ice can help with any post-procedure discomfort.
Most patients begin noticing improvement within one to two weeks, with full benefit appearing over the subsequent 4 to 6 weeks. Pain relief most commonly lasts approximately 6 months, though some patients report benefit for up to 12 months. If you had significant improvement from an initial course, repeat treatment is an option when pain returns. If you did not respond meaningfully, your provider will discuss alternative approaches rather than recommending a repeat course without evidence of benefit.
Preparing for Your Appointment
- Bring your insurance card and photo ID
- Bring a complete list of current medications and supplements
- Wear loose, comfortable clothing that allows easy access to the knee
- Arrive 15 minutes early to complete paperwork
- Inform your provider of any allergies, including to poultry products
- Arrange for a driver if you prefer, though most patients drive themselves home
Understanding Your Treatment Options
Knee OA has several management options, each with real benefits and known limitations. Understanding all of them helps you make an informed decision rather than feeling pressured toward any single path.
| Tratamiento | Cómo funciona | Established Benefits | Limitations & Risks |
|---|---|---|---|
| NSAIDs / Acetaminophen | Reduce pain and inflammation systemically | Proven symptom relief; guideline-recommended first line; low cost; widely accessible | Does not address joint lubrication or structure; long-term NSAID use carries GI, renal, and cardiovascular risks; acetaminophen carries liver risk at high doses |
| Inyecciones de corticosteroides | Powerful local anti-inflammatory | Rapid, meaningful short-term relief; guideline-supported; useful for acute flares | Short duration (weeks to months); repeated use may accelerate cartilage loss; risk of blood sugar elevation, tendon weakening, joint infection (rare) |
| Fisioterapia | Strengthens periarticular muscles; improves biomechanics | Guideline-recommended; addresses functional deficits; durable benefits; no systemic side effects | Requires consistent participation; may not fully resolve severe symptoms; slower onset of benefit |
| Inyecciones de ácido hialurónico | Supplements synovial fluid viscosity | FDA-approved for knee OA; modest but clinically meaningful pain relief; good safety profile; non-surgical | Modest effect size in most meta-analyses; less effective in severe OA; injection site reactions possible; results vary by patient; AAOS 2021 CPG gives “inconclusive” recommendation |
| Terapia PRP | Concentrated growth factors support tissue healing | Some evidence for pain reduction; uses patient’s own blood | Not FDA-approved as a drug for knee OA; evidence is mixed; not covered by most insurance |
| Surgery (Knee Replacement) | Replaces damaged joint surfaces | Highly effective for end-stage OA; restores function; durable outcomes | Invasive; recovery of weeks to months; surgical risks (infection, blood clots, nerve damage, implant failure); not all patients are candidates |
How Joint Health Solutions Approaches Knee OA
We evaluate each patient individually to determine which treatments best match their OA severity, prior treatment history, functional goals, and overall health.
Inyecciones de ácido hialurónico
Inyecciones de ácido hialurónico are our primary viscosupplementation option for knee OA and the central focus of this article. We use FDA-approved products and administer them using fluoroscopic guidance to confirm accurate needle placement in the joint space.
Inyecciones guiadas por fluoroscopia
Fluoroscopy-guided injection uses real-time imaging to confirm the needle is positioned correctly before the medication is delivered. This is particularly important when joint space narrowing makes access more challenging, or when prior injections have not reached the intended location.
Inyecciones de cortisona
Inyecciones de corticoides are used when acute inflammation needs to be addressed rapidly. They can provide meaningful short-term relief and allow patients to engage more effectively in physical therapy. We use them judiciously to avoid the risks of repeated administration.
Terapia PRP
Terapia con PRP may be an option for patients who have not responded to HA injections or who want to explore additional regenerative approaches. Evidence in knee OA is mixed; candidacy and evidence are discussed transparently before proceeding.
Rodilleras de descarga
Descarregar los tirantes de rodilla redistribute mechanical load away from the most damaged compartment of the joint, reducing pain with activity. They work well alongside injection therapy for patients with compartmental OA.
Fisioterapia
Fisioterapia is foundational to knee OA management and recommended by all major clinical guidelines. We coordinate care with physical therapists to support long-term function alongside injection therapy.
Evidence and Clinical Research
| Component | FDA Status | Evidence Level | Key Findings |
|---|---|---|---|
| Hyaluronic Acid Injections — Knee OA | FDA-approved for knee OA pain (Synvisc, Euflexxa, Orthovisc, HYMOVIS, TriVisc, and others) | Established clinical evidence (multiple meta-analyses) | Modest but clinically meaningful pain relief and functional improvement; most studies show benefit to approximately 6 months; some products and patients report benefit up to 12 months; good safety profile; most effective in mild to moderate OA |
| High vs. Low Molecular Weight HA Formulations | Both FDA-approved; multiple products available | Limited / mixed evidence | Some studies suggest higher molecular weight may provide superior lubrication; comparative clinical outcome data across products is inconsistent; no clear superiority established in head-to-head trials |
| Single-Injection vs. Multi-Injection Regimens | Both FDA-approved (product-dependent) | Established clinical evidence | Both regimens demonstrate efficacy in clinical trials; the optimal number of injections depends on product and patient; no strong evidence that multi-injection is superior to single-injection products when each is used as indicated |
Important: Hyaluronic acid injections do not reverse cartilage loss or cure osteoarthritis. They are a symptomatic treatment. Individual results vary, and not every patient is a candidate or will respond.
Preguntas frecuentes
¿Cuánto tiempo duran las inyecciones de ácido hialurónico?
La mayoría de los estudios clínicos muestran una reducción significativa del dolor durante aproximadamente 6 meses. Algunos pacientes y productos muestran beneficios que se prolongan hasta 12 meses, especialmente con formulaciones de mayor peso molecular. La duración depende de la gravedad de la OA, el nivel de actividad, el peso corporal y la respuesta individual. No todos los pacientes responden, y la duración del beneficio varía considerablemente.
¿Las inyecciones de ácido hialurónico son dolorosas?
La mayoría de los pacientes reportan solo un leve malestar durante la inyección — similar a una extracción de sangre. Puede utilizarse un spray anestésico o un anestésico local. Después de la inyección, una leve doloridad, calidez o hinchazón en el lugar es común pero generalmente desaparece en un plazo de 48 a 72 horas.
¿Cuántas inyecciones necesitaré?
Esto depende del producto específico seleccionado. Algunos están diseñados como tratamientos con una sola inyección; otros incluyen una serie de 3 inyecciones semanales. Su proveedor recomendará el producto y el régimen adecuados en función de su evaluación clínica y de la cobertura asegurada.
¿Puedo recibir inyecciones de HA si tengo artritis grave (artritis entre huesos)?
Los pacientes con OA en etapa final suelen responder de forma menos predecible a la viscosaumentación. No está contraindicada en todos los casos, pero los resultados clínicos son menos consistentes que en la OA leve a moderada. Su médico revisará sus imágenes y analizará si el posible beneficio justifica el tratamiento o si una consulta quirúrgica es el paso siguiente más adecuado.
¿Cuál es el tiempo de recuperación?
No se requiere un tiempo de inactividad. Recomendamos evitar ejercicios intensos, levantar objetos pesados o permanecer de pie durante largos períodos durante las primeras 48 horas. El hielo puede ayudar a aliviar cualquier molestia que pueda surgir tras la inyección. La mayoría de los pacientes pueden volver a trabajar en la oficina y realizar otras actividades diarias al día siguiente.
¿Hay algún efecto secundario?
Los efectos secundarios más comunes son leves y temporales: dolor en la zona de la inyección, hinchazón, calidez o enrojecimiento durante un máximo de unos pocos días. En un pequeño porcentaje de pacientes se produce una erupción postinyección —un aumento transitorio de la intensidad del dolor y la hinchazón—. Las complicaciones graves, como infecciones articulares, son raras. Su médico le explicará todos los riesgos antes del tratamiento.
¿Pueden las inyecciones de HA combinarse con otros tratamientos?
Sí. Las inyecciones de HA suelen utilizarse junto con la fisioterapia, el uso de férulas para el rodilla y planes nutricionales. Algunos pacientes también discuten la terapia con PRP como una alternativa o complemento. Su proveedor elaborará un plan personalizado en función de su condición y objetivos.
¿Esto está cubierto por la póliza de seguro?
Many Medicare plans and commercial insurers cover hyaluronic acid injections for knee OA when conservative care is documented and medical necessity criteria are met. Coverage varies by plan. Our team can verify your benefits before your appointment. Call us at 704-833-3566.
¿Cuándo comenzaré a sentir alivio?
Some patients notice improvement within one to two weeks; for those receiving a series of injections, benefit often builds after each dose. Full benefit is typically assessed 4 to 6 weeks after the last injection in the series.
What if the injections don’t work for me?
If you do not experience adequate relief after a course of HA injections, your provider will discuss what options remain — including cortisone injections for acute flares, PRP therapy, continued physical therapy, or, when appropriate, a surgical consultation. We will not recommend indefinitely repeating treatment that has not provided benefit.
Crea una cita para una consulta en Charlotte
If you recognize any of the signs described above and conservative care has not provided adequate relief, Joint Health Solutions can evaluate whether hyaluronic acid injections or another non-surgical approach may be appropriate for your knee.
📞 Call us: 704-833-3566
What to bring to your first visit: recent knee imaging (X-ray or MRI reports if available), a current medication and supplement list, notes on prior treatments and their outcomes, and your insurance card.
Fuentes
FDA Product Approvals
- FDA — HYMOVIS® ONE Premarket Approval
- FDA — TriVisc Premarket Approval
- FDA — Synvisc Premarket Approval
Key Clinical References
- Bannuru RR, et al. (2019). OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. PubMed: 31278997
- Huang Y, et al. (2021). Efficacy and safety of intra-articular hyaluronic acid injection for knee osteoarthritis. Journal of Orthopaedic Surgery and Research. PubMed: 34011337
- Altman RD, et al. (2015). The mechanism of action for hyaluronic acid treatment in the osteoarthritic joint. BMC Musculoskeletal Disorders. PubMed: 26578847
- American Academy of Orthopaedic Surgeons. (2021). Management of Osteoarthritis of the Knee: Evidence-Based Clinical Practice Guideline, 4th Edition. AAOS CPG 2021 — Viscosupplementation: “Inconclusive” recommendation
Fuentes institucionales
- Mayo Clinic — Hyaluronic Acid Injection Route
- Hospital for Special Surgery (HSS) — Viscosupplementation for Knee Osteoarthritis
- Arthritis Foundation — Hyaluronic Acid Injections
Disclaimer: This content is for informational purposes only and does not constitute medical advice. Always consult with a qualified healthcare provider to determine whether hyaluronic acid injections are appropriate for your specific condition. Individual results vary, and not every patient is a candidate. The AAOS 2021 Clinical Practice Guideline for knee OA gives an “inconclusive” recommendation for viscosupplementation, reflecting variability in trial results. This does not mean the treatment is ineffective for all patients; multiple systematic reviews support modest benefit in selected individuals.



 Spanish
 English