Restoring Shock Absorption: Hyaluronic Acid Injections for Active Adults with Knee Arthritis
Published July 10, 2026 | Last reviewed: July 14, 2026 | Category: Joint Health, Non-Surgical Treatments | Location: Charlotte, NC
🕒 15 MIN READ
You used to run five miles without a second thought. Now, every step on your morning walk feels like grinding gravel inside your knee. The stiffness after sitting, the sharp twinge when you go downstairs, the dull ache that keeps you awake at night — if this sounds familiar, you are not alone. Millions of active adults live with knee arthritis. But reduced activity does not have to be permanent.
For many patients with mild to moderate knee arthritis, hyaluronic acid injections (viscosupplementation) are a non-surgical option that may help restore the knee’s natural lubrication and reduce pain. This article explains how the treatment works, what the evidence shows, who may be a candidate, and what to expect at Joint Health Solutions in Charlotte.
Quick Answer
FDA-approved hyaluronic acid products are typically administered as a series of one to three injections spaced about one week apart. Some patients report pain relief lasting several months; duration and degree of response vary by individual, arthritis severity, and the specific product used. Not all patients experience meaningful benefit. Good candidates typically have mild to moderate knee osteoarthritis and have not found adequate relief from first-line treatments such as physical therapy, weight management, or over-the-counter medications. A clinical evaluation is needed to determine whether this treatment is appropriate.
Why Knee Arthritis Develops: The Biology
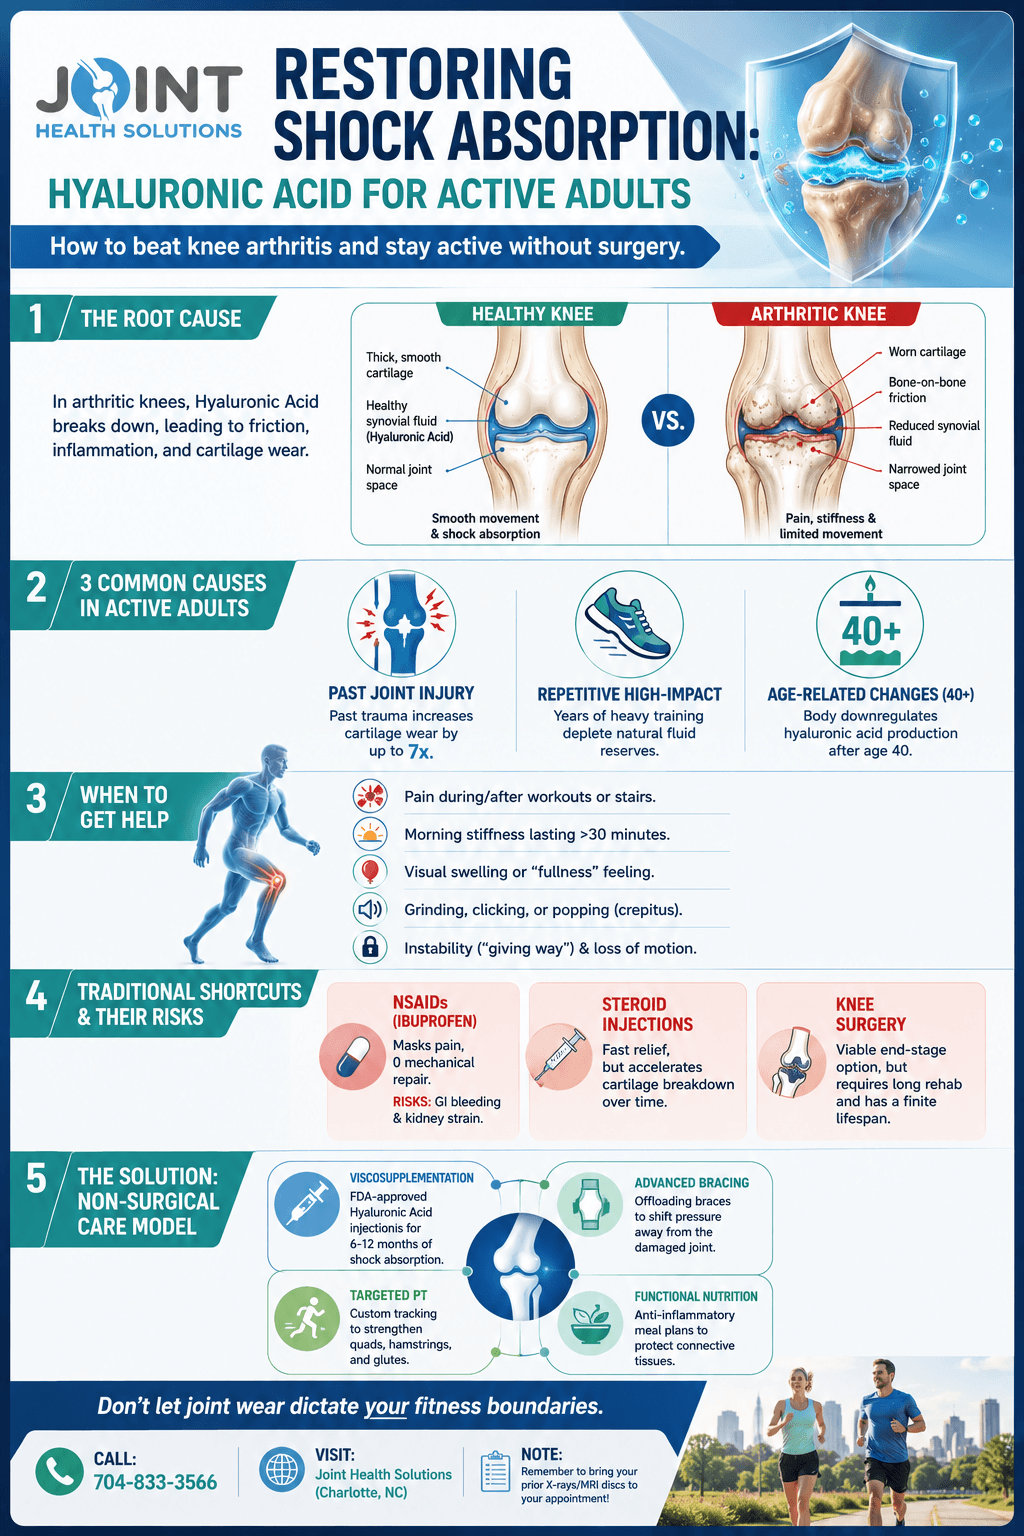
Healthy joints rely on synovial fluid — a thick, gel-like substance that cushions and lubricates the joint for smooth movement. This fluid gets much of its viscosity and elasticity from hyaluronic acid, a naturally occurring molecule that acts as both a lubricant and a shock absorber.
In arthritic knees, the concentration and molecular weight of hyaluronic acid in the synovial fluid decrease. As cartilage breaks down, joint space can narrow, leading to increased friction and pain. The role of synovial fluid changes in the progression of knee osteoarthritis is well established, though the degree to which supplementing the fluid can influence the disease course remains an active area of research.
3 Common Causes of Knee Arthritis in Active Adults
1. Previous Joint Injury
Past trauma — such as a torn meniscus, ACL rupture, or patellar dislocation — can alter the joint’s natural alignment and mechanics. Research indicates that individuals with a prior significant knee injury have a meaningfully higher risk of developing osteoarthritis earlier, even after complete rehabilitation. The specific risk increase varies by injury type, severity, and other individual factors.
2. Repetitive High-Impact Activity
Years of high-impact training (long-distance running, basketball, heavy strength work) place repetitive stress on the cartilage and surrounding structures. Over time, without adequate recovery, this can accelerate cartilage wear. The relationship between activity level, injury history, and OA development is individual and not uniform.
3. Age-Related Changes
As we age, natural production of hyaluronic acid and the repair capacity of cartilage tissue decline. For active adults, this gradual shift can accelerate the transition from manageable stiffness to symptomatic osteoarthritis. Age is the single strongest risk factor for knee OA.
Symptoms That Suggest a Clinical Evaluation
The following symptoms may indicate knee osteoarthritis and warrant professional evaluation:
- Pain during or after weight-bearing activities (walking, running, stair climbing)
- Morning stiffness or stiffness after rest lasting more than 30 minutes
- Visible swelling or a sensation of pressure within the knee
- A grinding, clicking, or popping sensation (crepitus) during movement
- Reduced range of motion — difficulty fully extending or bending the knee
- A sense of instability or the knee “giving way”
These symptoms can also result from other conditions, including meniscus tears, ligament injuries, gout, or inflammatory arthritis. A proper evaluation is needed to identify the cause before selecting a treatment approach.
Understanding Your Treatment Options
Knee osteoarthritis management typically follows a stepped approach. Understanding where each option fits helps patients and providers make informed decisions together.
Oral Medications (NSAIDs and Acetaminophen)
Non-steroidal anti-inflammatory drugs (ibuprofen, naproxen) and acetaminophen are common first-line options for knee OA pain. They can provide meaningful symptom relief and have well-established evidence. Long-term NSAID use carries risks of gastrointestinal, kidney, and cardiovascular effects, which is why ongoing use should be monitored by a healthcare provider. These medications address symptoms but do not alter the underlying joint structure.
Corticosteroid Injections
Corticosteroid (steroid) injections deliver a powerful anti-inflammatory effect directly to the joint. They have established evidence for short-term pain relief and can be particularly useful for managing acute flares. Duration of effect is typically weeks to a few months. Frequent, repeated injections over time may have adverse effects on cartilage and surrounding tissue, so most providers recommend using them judiciously and not as a long-term sole strategy.
Hyaluronic Acid Injections (Viscosupplementation)
Hyaluronic acid injections work by supplementing the synovial fluid rather than primarily suppressing inflammation. FDA-approved products are available for knee OA pain in patients who have not responded to conservative therapy. They are not appropriate for all patients — particularly those with advanced bone-on-bone arthritis — and clinical guidelines vary on their use. See the evidence section below for detail.
Surgery
Surgical options, including arthroscopy and knee replacement, are well-established for appropriate patients. Total knee replacement is one of the most studied and effective interventions for end-stage knee OA, with documented improvements in pain and function. Surgery is generally considered after conservative treatments have been exhausted and when joint damage is advanced. It carries standard surgical risks and requires a rehabilitation period. For younger or highly active patients, delaying surgery while maintaining function is often a shared goal, but surgery should not be dismissed as an option when it is clinically appropriate.
How Hyaluronic Acid Injections Compare to Other Options
| Treatment | How It Works | Evidence Level | Limitations | When Appropriate |
|---|---|---|---|---|
| Oral NSAIDs / Acetaminophen | Reduce pain and inflammation | Established clinical evidence | Does not address underlying joint structure; long-term use carries systemic risks | First-line symptom management |
| Corticosteroid Injections | Powerful local anti-inflammatory effect | Established clinical evidence for short-term relief | Short duration; frequent use may have adverse cartilage effects | Acute flare management; selected patients |
| Hyaluronic Acid Injections | Supplements synovial fluid lubrication | FDA-approved; mixed clinical guideline recommendations | Results vary; not effective for advanced OA; requires repeat treatment cycles | Mild-to-moderate OA; failed first-line care |
| Physical Therapy | Strengthens supporting muscles; improves mechanics | Established clinical evidence; guideline-recommended | Requires adherence and time | All stages; foundational care |
| Surgery (Arthroscopy / Knee Replacement) | Removes damaged tissue or replaces joint | Established evidence for appropriate candidates | Invasive; recovery time; not appropriate for all patients or stages | Advanced OA; failure of conservative care |
The Science: What the Evidence Shows
Viscosupplementation has been evaluated in numerous clinical trials and systematic reviews. The overall picture is one of modest benefit in appropriate candidates, with meaningful variation across studies.
A 2015 systematic review published in the Journal of Bone and Joint Surgery (Jevsevar et al.) evaluated the available evidence and found that hyaluronic acid injections produced statistically significant improvements in pain and function compared to control, though the clinical magnitude of effect varied across populations. A 2019 systematic review and meta-analysis (Bannuru et al., Osteoarthritis and Cartilage) similarly found that viscosupplementation reduced pain more than placebo at several time points, though effect sizes were modest.
The AAOS Clinical Practice Guideline for Management of Osteoarthritis of the Knee (2021) provides an inconclusive recommendation for hyaluronic acid, meaning existing evidence does not clearly support or refute its use for all patients. This reflects genuine variation in study results rather than a definitive verdict. Some patients experience meaningful benefit; others do not.
Laboratory studies have suggested that high-molecular-weight hyaluronic acid may have chondroprotective properties — meaning it may help protect cartilage cells from further damage. This is a biologically plausible mechanism, but its clinical relevance in humans has not been fully established, and hyaluronic acid injections are not FDA-approved for cartilage protection or disease modification.
Evidence Table: Hyaluronic Acid Injections for Knee Osteoarthritis
| Component | FDA Status | Evidence Level | Key Findings |
|---|---|---|---|
| Hyaluronic Acid Injections — Knee OA Pain | FDA-approved for knee OA pain in patients who failed conservative therapy | Established clinical evidence (multiple trials and meta-analyses) | Modest pain relief and functional improvement; good safety profile; duration and degree of response vary |
| Higher Molecular Weight Formulations | FDA-approved (device or drug, product-specific) | Established clinical evidence | May provide superior lubrication compared to lower molecular weight forms; comparative evidence is limited |
| Chondroprotective Effects | Not an FDA-approved indication | Emerging / mechanistic evidence | Laboratory studies suggest HA may protect cartilage cells; clinical relevance in humans not established |
| Anti-inflammatory Effects in Synovial Fluid | Not a separate FDA indication | Emerging / mechanistic evidence | May reduce inflammatory markers in joint fluid; clinical significance requires further study |
Evidence-Level Definitions:
- FDA-approved: Received FDA approval for a specific indication.
- Established clinical evidence: Supported by multiple peer-reviewed human studies.
- Emerging / mechanistic: Early-stage or laboratory research suggesting a mechanism; not yet established as a clinical benefit in humans.
Treatment Approach at Joint Health Solutions
At Joint Health Solutions, we provide a comprehensive evaluation before recommending any injection therapy. Our approach combines several non-surgical options when appropriate.
Viscosupplementation
When a patient is a candidate, we administer FDA-approved hyaluronic acid directly into the knee joint under appropriate technique. The procedure is performed in-office. A typical course involves one to three injections spaced approximately one week apart, depending on the product used. Some patients report improvement within a few weeks; others may take longer or may not respond. We discuss realistic expectations before starting treatment.
Learn more about our hyaluronic acid injection service.
Offloading Knee Braces
For patients with osteoarthritis predominantly on one side of the joint, an offloading knee brace can shift structural load away from the damaged compartment, reducing pain during activity. Bracing is often used alongside injection therapy rather than in isolation.
Physical Therapy
Strengthening the muscles around the knee — particularly the quadriceps, hamstrings, and glutes — reduces mechanical stress on the joint. Our providers coordinate with physical therapists to build individualized programs based on each patient’s goals, baseline function, and activity level. Explore our physical therapy services.
Nutrition Support
An anti-inflammatory dietary pattern may help reduce systemic inflammation that can amplify joint pain. We offer nutrition plans as one component of a comprehensive management strategy. Diet does not cure arthritis or reverse structural damage, but it can support overall health and may complement other treatments.
What to Expect at Your First Appointment
Your first visit begins with a thorough evaluation of your knee pain history, symptom pattern, prior treatments, medications, and activity goals. We will perform a physical examination of the knee and, if you do not have recent imaging, discuss whether X-rays or an MRI would be useful to confirm diagnosis and severity.
If you are a candidate for hyaluronic acid injections, we will explain the procedure, the expected timeline, and what outcomes are realistic for your specific situation. The injection itself involves a thin needle and typically takes a few minutes. Most patients tolerate it well. Some experience mild soreness or swelling at the injection site for one to two days. We advise avoiding high-impact activities (running, heavy lifting) for 48 hours after each injection.
We will schedule follow-up to assess your response and determine whether additional treatments are appropriate. Not all patients respond to viscosupplementation, and we will discuss next steps clearly if the initial series does not produce meaningful improvement.
Who Is a Candidate for Hyaluronic Acid Injections?
Patients who tend to be the best candidates share the following profile:
- Mild to moderate knee osteoarthritis confirmed by imaging (typically Kellgren-Lawrence grade 1–3)
- Inadequate relief from first-line treatments (physical therapy, NSAIDs, weight management)
- Not appropriate for or not yet ready for surgical intervention
- No active joint infection or known allergy to hyaluronic acid products
Patients with severe bone-on-bone arthritis (grade 4) tend to respond less well to viscosupplementation, and surgical evaluation may be the more appropriate next step. A thorough evaluation is required before any injection recommendation.
Questions to Ask Before Starting Hyaluronic Acid Injections
- Am I a good candidate given the severity of my arthritis?
- Which FDA-approved product will be used, and why?
- How many injections will I need and how far apart?
- What outcomes are realistic for someone with my grade of OA?
- How will we know if the treatment is working?
- What is the plan if I don’t respond?
- Is this covered by my insurance?
- Can I combine this with physical therapy or other treatments?
Frequently Asked Questions
How long do hyaluronic acid injections last?
Duration of response varies. Some patients report pain relief for six months or longer; others experience a shorter benefit or do not respond. Duration depends on the severity of arthritis, the product used, activity level, and individual factors. Some patients who respond well choose to repeat the treatment cycle annually, though this should be discussed with your provider based on your specific situation.
Are hyaluronic acid injections painful?
The injection involves a thin needle and is generally well-tolerated. We use appropriate technique to minimize discomfort, which may include cooling or local numbing. Most patients describe mild pressure during the procedure rather than sharp pain. Some soreness or mild swelling at the injection site afterward is normal and typically resolves within one to two days.
Can I exercise after getting hyaluronic acid injections?
We recommend avoiding high-impact activities (running, jumping, heavy resistance training) for 48 hours after each injection. Low-impact activities such as walking, swimming, or cycling are generally fine. Your provider will give specific guidance based on your condition and the injection site.
How many injections will I need?
The standard course involves one to three injections given approximately one week apart, depending on the FDA-approved product selected. Some newer single-injection formulations require only one visit. Your provider will recommend a protocol based on the product and the clinical picture.
Does insurance cover hyaluronic acid injections?
Many insurance plans cover FDA-approved hyaluronic acid injections for knee osteoarthritis, particularly when prior conservative treatment has been documented. Coverage varies by plan and may require prior authorization. Our team can verify your insurance benefits before your appointment. Call us at 704-833-3566 to discuss.
Who is a good candidate?
Good candidates typically have mild to moderate knee osteoarthritis (confirmed by X-ray or MRI), have not found adequate relief from first-line treatments such as physical therapy or NSAIDs, and are not appropriate candidates for or not yet ready for surgery. Patients with severe bone-on-bone arthritis may not respond as well. A clinical evaluation is required to determine candidacy.
Are there side effects?
Side effects are generally mild and temporary. The most common include injection site pain, swelling, warmth, or redness, which usually resolve within a few days. Serious complications such as infection are rare. A small subset of patients may experience a local inflammatory reaction (pseudoseptic reaction). Your provider will discuss all potential risks before treatment.
Can I have hyaluronic acid injections if I have had steroid injections before?
Yes, though most providers recommend allowing a washout period of several weeks to months after a corticosteroid injection before proceeding with hyaluronic acid. Steroids can temporarily alter the joint environment. Your provider will advise on appropriate timing based on your history.
Will hyaluronic acid injections help me avoid knee replacement surgery?
For some patients, viscosupplementation provides relief that allows them to delay or avoid surgery. However, it is not a cure and cannot reverse advanced joint damage. Patients with end-stage arthritis may ultimately require surgical evaluation regardless of injection outcomes. The goal is to manage symptoms and maintain function for as long as possible through appropriate non-surgical care.
How soon will I feel relief after the injection?
Some patients notice improvement within a few days. Others take two to four weeks to experience meaningful benefit, as the hyaluronic acid needs time to integrate with the joint’s natural fluid environment. Completing the full recommended injection series is generally more effective than stopping after one injection. Patients who do not notice improvement after completing the series should discuss next steps with their provider.
What does “FDA-approved” mean for hyaluronic acid products?
It means the specific product has been reviewed and approved by the FDA for the treatment of knee osteoarthritis pain in patients who have not responded adequately to conservative therapy. FDA approval indicates safety and efficacy were demonstrated in clinical studies for that specific indication and population. It does not mean the product works for every patient or for all stages of osteoarthritis.
Is hyaluronic acid the same as a steroid shot?
No. Corticosteroid (steroid) injections primarily reduce inflammation and provide short-term pain relief. Hyaluronic acid injections supplement the joint’s lubricating fluid and work differently. They are sometimes used together or sequentially, depending on the clinical picture, but they are distinct treatments with different mechanisms, timelines, and indications.
Schedule a Consultation in Charlotte
If knee pain is limiting your activity, our board-certified providers at Joint Health Solutions can evaluate your condition and discuss whether hyaluronic acid injections or another non-surgical approach may be appropriate for you.
📞 Call us: 704-833-3566
What to bring to your first visit:
- Any prior knee imaging (X-ray discs, MRI reports)
- A list of current medications and supplements
- Notes on your symptoms — when they occur, what makes them better or worse
- Your insurance card and photo ID
- Questions for the provider about your condition and treatment options
Sources
Institutional and Guideline Sources
- Mayo Clinic — Osteoarthritis: Diagnosis and Treatment
- Hospital for Special Surgery (HSS) — Viscosupplementation for Knee Osteoarthritis
- Arthritis Foundation — Osteoarthritis
- National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS) — Osteoarthritis
Key Clinical References
- Jevsevar D, et al. (2015). Viscosupplementation for Osteoarthritis of the Knee: A Systematic Review of the Evidence. Journal of Bone and Joint Surgery. PubMed: 26491131
- Bannuru RR, et al. (2019). OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. PubMed: 31278997
- Trigkilidas D, Rankin A. (2012). The effectiveness of hyaluronic acid intra-articular injections in managing osteoarthritic knee pain. Annals of the Royal College of Surgeons of England. PubMed: 23031763
- Altman RD, Manjoo A, Fierlinger A, et al. (2015). The mechanism of action for hyaluronic acid treatment in the osteoarthritic knee: a systematic review. BMC Musculoskeletal Disorders. PubMed: 26578847
Disclaimer: This content is for informational purposes only and does not constitute medical advice. Always consult with a qualified healthcare provider to determine whether these treatments are appropriate for your specific condition. Individual results vary, and not every patient is a candidate for every treatment described. All medical claims and provider experience statements should be verified by Joint Health Solutions before publication.