
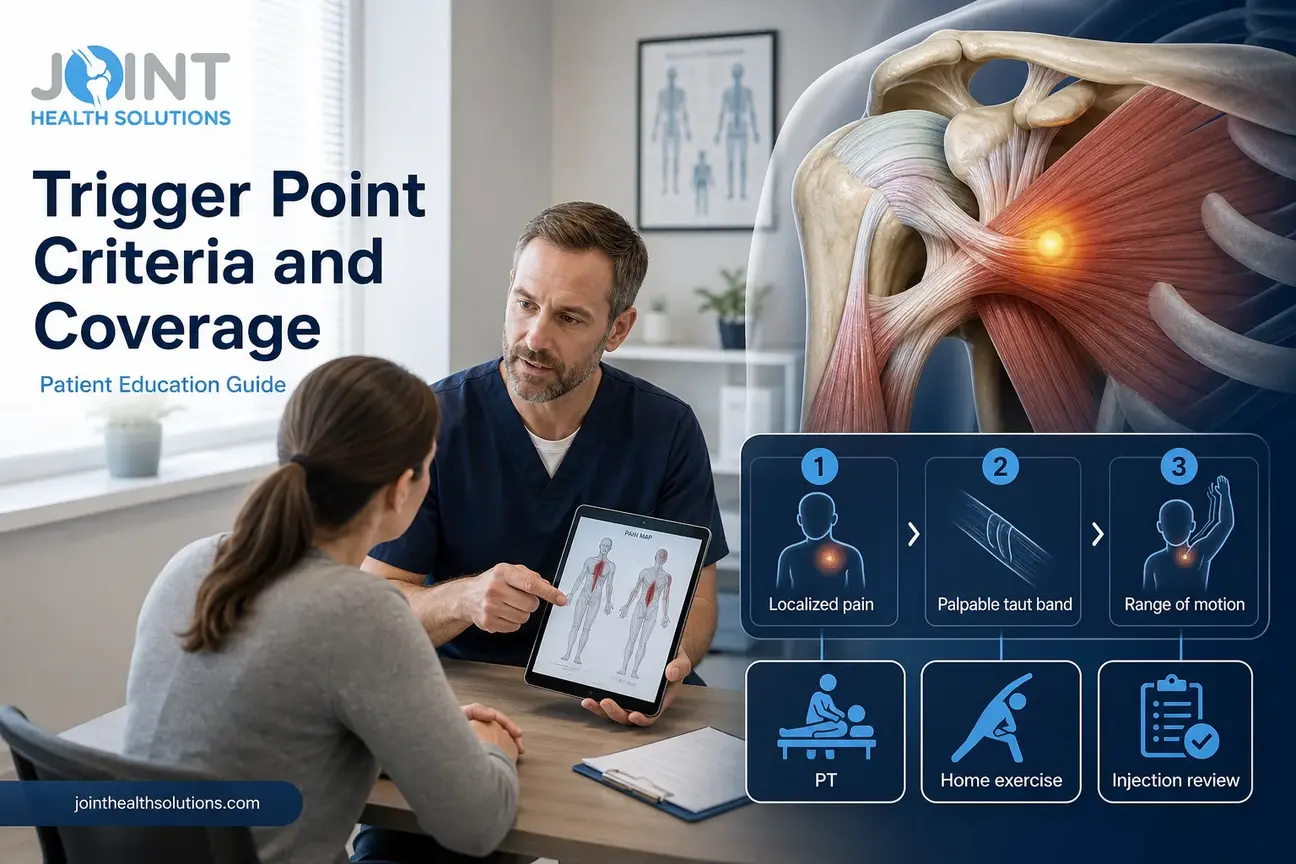
Trigger Point Injection Criteria and Coverage Basics
Quick Answer: trigger point injection criteria usually focus on documented localized muscle pain, exam findings consistent with myofascial trigger points, a palpable taut band or tender nodule, functional limits such as restricted motion, and a reasonable trial of conservative care when appropriate. Coverage is not automatic; payer rules vary, repeat treatment requirements can differ, and documentation often matters as much as the injection itself.
If you are comparing options before scheduling, it helps to think of trigger point injections as one possible part of a broader treatment plan, not a stand-alone fix for every kind of muscle or joint pain. At Joint Health Solutions, patients can learn more about trigger point injections and request an assessment when localized muscle knots or tension may be contributing to pain. If you are in Charlotte or traveling to the north Charlotte clinic, you can request an appointment or call 704-833-3566.
Quick comparison: criteria, coverage, and patient next steps
| Situation | Typical coverage or clinical position | What patients can do |
|---|---|---|
| Localized muscle pain with a tender knot | Trigger point injection criteria may be considered when the exam supports a focal trigger point rather than widespread or unclear pain. | Be ready to describe the exact pain location, what worsens it, and how it limits movement or daily activities. |
| Palpable taut band or nodule on exam | Many policies look for a documented tender band, nodule, or trigger point in skeletal muscle. | Ask what findings were documented and whether they match your plan’s medical necessity language. |
| Conservative care tried first | Payers often expect non-invasive care to be attempted, not tolerated, contraindicated, or insufficient before injections. | Keep records of physical therapy, home exercise, activity modification, medications, or other conservative measures you have tried. |
| Repeat treatment being considered | Repeat trigger point injections are commonly held to additional standards, and some policies may require documented benefit or set plan-specific limits. | Confirm plan-specific rules before another session and ask what improvement must be documented. |
| Medicare, VA, or commercial coverage question | Trigger point injection coverage varies by program, plan, payer policy, prior authorization rules, and documentation. | Verify benefits with the practice and insurer or benefits administrator before treatment and ask about covered and out-of-pocket costs. |
How trigger point injection criteria are usually evaluated
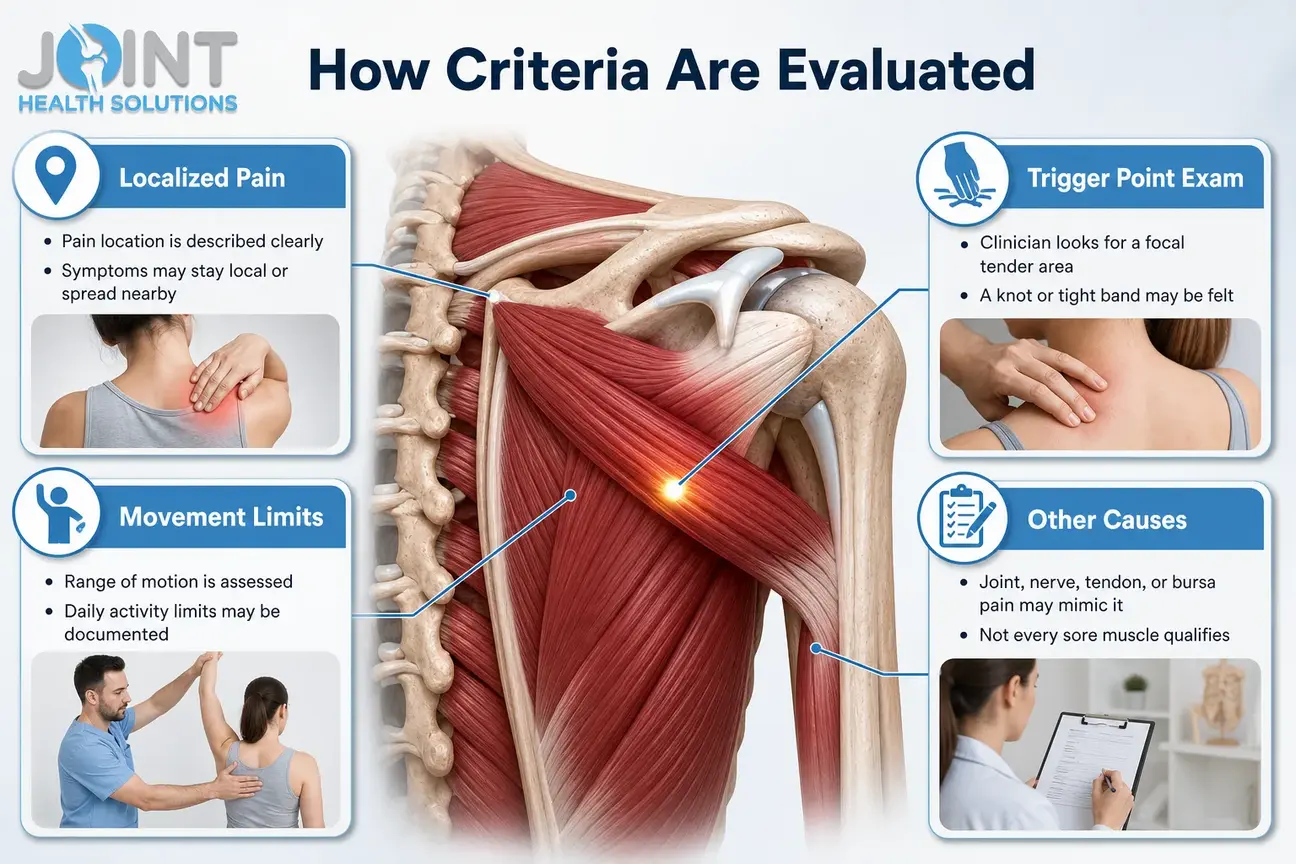
Trigger point injection criteria start with a clinical question: is the pain likely coming from a localized muscle trigger point that can be identified on exam? A trigger point is often described as a tender, focal area within skeletal muscle that may feel like a knot or tight band. Some patients notice pain directly at that spot, while others feel discomfort that spreads into a nearby region. A clinician still needs to evaluate whether the pattern fits myofascial pain and whether another cause should be considered.
Coverage documents do not treat every sore muscle as a qualifying trigger point. In general, payer policies tend to focus on the clinical record: where the pain is located, what the exam shows, how function is affected, and what conservative therapy has already been tried or considered. This article does not state a Medicare trigger point injection LCD checklist or repeat-session cap because the client profile does not contain a verified North Carolina trigger point injection LCD entry for use in publication.
The phrase “trigger point injection criteria” can sound like a simple checklist, but real-world decisions are more nuanced. A clinician may consider where the pain is, whether the muscle finding is reproducible, whether range of motion is limited, whether conservative care has been tried, and whether the injection would fit into an individual treatment plan. Payers may also look for documentation that the injection is not being used as an isolated or open-ended service.
Myofascial trigger points and localized pain patterns
Myofascial trigger points are commonly discussed in the context of muscle pain, tension, and restricted movement. They may be associated with tender spots in skeletal muscle that are painful when pressed and may contribute to guarding, tightness, or limited motion. Because pain can come from many sources, including joints, nerves, tendons, bursae, and referred pain patterns, the presence of muscle discomfort alone is not enough to determine whether a trigger point injection is appropriate.
For adults already dealing with knee, shoulder, hip, back, or other musculoskeletal pain, this distinction matters. Joint arthritis or degenerative joint disease can coexist with muscle guarding, but that does not automatically mean injections for muscle knots are the right next step. A clinical assessment helps separate joint-driven pain, muscle-related pain, and other possible contributors. That assessment also helps determine whether physical therapy, home exercise, injection therapy, bracing, or another conservative option may be appropriate.
When discussing trigger point injection criteria with a clinician, patients can ask whether the painful area is focal and reproducible, whether a specific muscle band or nodule is being documented, and whether the pain pattern fits a myofascial source. Those questions are practical because coverage policies often emphasize the exam finding, not just the patient’s description of discomfort.
Why focal skeletal-muscle findings matter
Focal findings help distinguish a trigger point from generalized soreness. A payer may want the record to show a defined area of pain in skeletal muscle, not simply a broad statement such as “neck pain” or “back pain.” The documentation may describe the affected muscle region, tenderness, the patient’s pain response during exam, and any limitation in movement or function. This is one reason patients should be specific when explaining symptoms.
A clear exam also helps avoid overusing injections when the pain source is unclear. Trigger point injections may be considered when appropriate, but they are not a universal answer for all stiffness, arthritis pain, or mobility limitations. In evidence-informed care, the goal is to match the treatment to the likely pain generator and the patient’s overall condition. In that context, trigger point injection criteria help keep the discussion focused on the exam and the treatment plan.
Palpable taut band documentation and medical necessity
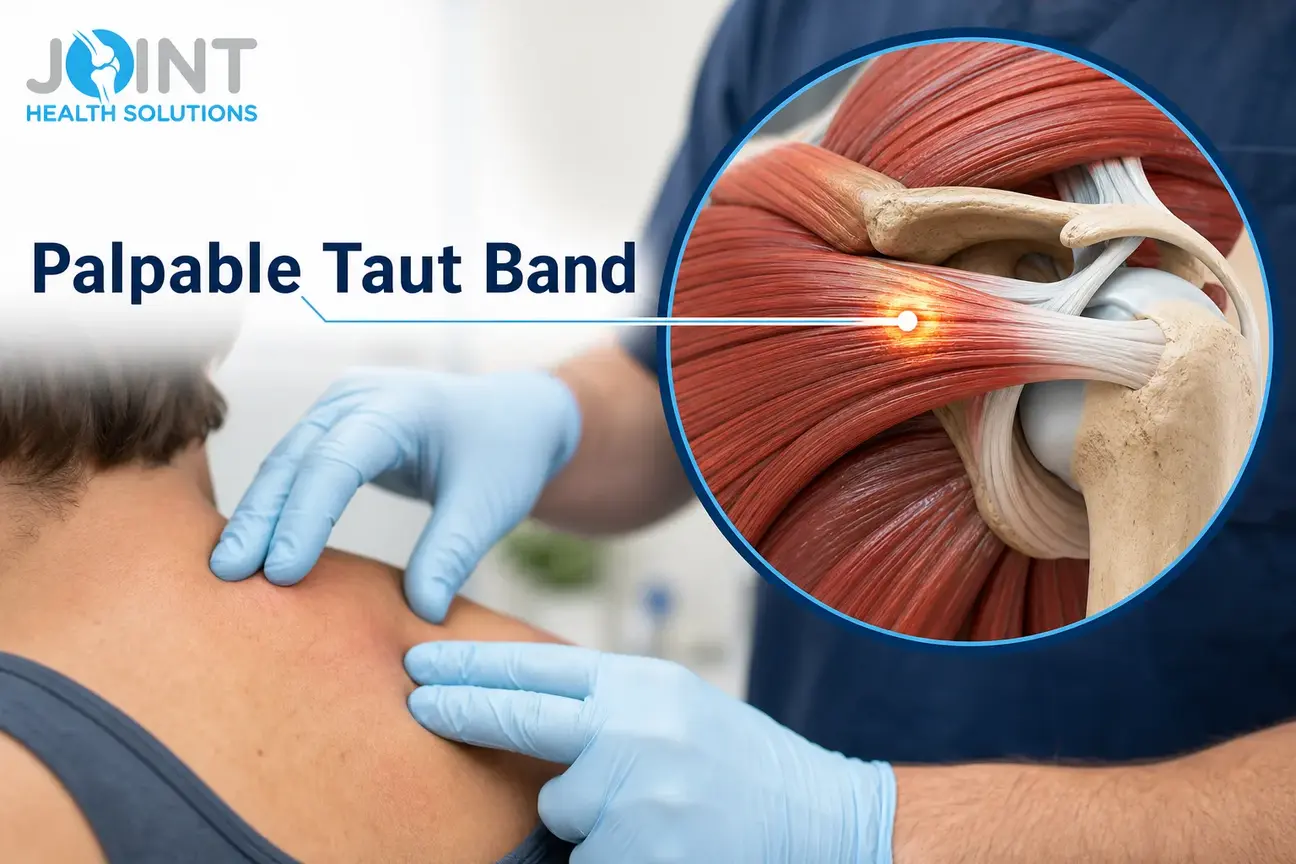
A palpable taut band is one of the most common phrases patients encounter when researching trigger point injection criteria. In plain language, it refers to a tight, tender band or nodule that can be felt during a physical exam. Coverage policies may use similar wording, such as a hypersensitive bundle, nodule, tender point, or taut band in muscle. The exact terms vary, but the underlying idea is that the trigger point should be clinically identifiable.
Documentation of a palpable taut band is not just a technical billing detail. It helps support why an injection is being considered instead of, or alongside, other forms of conservative care. It also gives the patient and clinician a clearer target for treatment planning. If the painful area cannot be localized or the exam does not support myofascial trigger points, the care plan may need to focus on further evaluation or a different treatment approach.
Patients should be cautious when reading Medicare LCDs, billing articles, or insurer policies found online. A policy may be written for a different jurisdiction, a different plan type, or a different effective date. For a Charlotte audience, this distinction matters because Original Medicare local coverage policies can be administered by specific Medicare Administrative Contractors, and Medicare Advantage or commercial plans may use their own plan documents and authorization processes.
What the medical record may need to show
The medical record may need to connect the patient’s symptoms, exam findings, and care plan. That can include the location of pain, the muscle area involved, functional effects, conservative treatments attempted, and the reason an injection is being considered. For repeat care, the record may also need to document response to prior treatment and why another injection is reasonable within the plan’s rules.
Patients can help by bringing a concise history. Useful details may include when symptoms started, whether pain is localized or widespread, which movements are limited, what conservative measures have been tried, and whether prior treatment helped daily function. This is not about “proving” pain; it is about giving the clinician and payer enough information to understand medical necessity and whether trigger point injection criteria may be documented.
Conservative therapy for muscle pain before injections
Conservative therapy for muscle pain often comes before injections, unless a clinician determines that a specific situation warrants a different approach. Conservative care may include physical therapy, a home exercise program, stretching, activity modification, heat or cold strategies, posture or movement changes, and other non-invasive options. The right combination depends on the patient’s condition, goals, medical history, and exam findings.
Coverage policies often ask whether conservative care was unsuccessful, not tolerated, contraindicated, or insufficient. This matters because trigger point injections are usually not viewed as a replacement for rehabilitation or functional restoration. Instead, they may be considered when a localized trigger point is contributing to pain or restricted motion and when injection therapy fits into a broader plan.
For patients at Joint Health Solutions, conservative care may include individualized assessment and, when appropriate, options such as physical therapy or other non-surgical care. The goal is not to rush every patient into an injection. The goal is to understand what is driving symptoms and choose a patient-centered plan that fits the clinical picture. Trigger point injection criteria are one part of that decision, not the whole decision.
Why an ongoing treatment plan matters
Many coverage policies and clinical discussions expect trigger point injections to be connected to an ongoing conservative treatment program rather than treated as an isolated service. The record may need to document participation in rehabilitation, a home exercise program, or functional restoration when appropriate. That reflects a broader principle: injections may help address a focal pain generator, but long-term function often depends on movement, strength, flexibility, and activity habits.
This is especially relevant for adults with joint pain, arthritis, degenerative joint disease, or stiffness. Muscle guarding may develop around a painful joint, and an injection may be considered for a focal muscle trigger point, but mobility and quality of life often require a broader plan. Patients should ask how an injection, if appropriate, fits with exercise, therapy, follow-up, and the trigger point injection criteria their plan may apply.
Trigger point injection coverage: Medicare, VA, and commercial plans
Trigger point injection coverage depends on the plan, the payer’s policy, documentation, medical necessity criteria, and sometimes prior authorization. A practice may accept certain insurance plans, but acceptance of a payer does not mean every procedure is covered for every patient. Covered and out-of-pocket costs should be reviewed before treatment, and patients should verify details with both the practice and their insurer.
Joint Health Solutions accepts Medicare, BlueCross BlueShield, Aetna, and Cigna as payers, according to the client profile. That participation should not be read as a procedure-level promise. A plan may cover one injection service under certain circumstances and not another, or it may require documentation before treatment. The safest approach is to verify the specific procedure, diagnosis, plan rules, authorization requirements, and expected patient responsibility before care begins.
Medicare examples are jurisdiction-specific and changeable
For Medicare-related coverage, patients should understand that CMS policies and billing articles are not the same as a blanket approval for every person. Original Medicare local coverage rules may depend on the Medicare Administrative Contractor for a given jurisdiction, and the relevant policy can change. Because this article does not include a verified North Carolina trigger point injection LCD from the client’s approved Medicare LCD policy list, it avoids stating procedure-specific Medicare criteria or a Medicare repeat-session limit for trigger point injections.
Medicare Advantage plans add another layer. They cover Medicare Part A and Part B benefits, but plan networks, prior authorization, cost sharing, and supplemental benefits can vary. CMS explains the general Medicare Advantage framework on its Health Plans general information page. Patients should review their Evidence of Coverage document and request plan-specific written confirmation when coverage is uncertain.
VA community care coverage basics
Veterans using VA benefits should not assume that community care is available simply because a non-VA clinic offers a service. VA community care eligibility is based on VA rules and authorization processes. The VA explains that Veterans may be eligible for community care in situations such as when VA does not offer the needed service, when access standards are not met, when the Veteran and VA provider agree community care is in the Veteran’s best medical interest, or when other VA criteria apply, as outlined in the VA’s eligibility for community care outside VA resource.
For practical purposes, that means a Veteran should work through VA channels before assuming a trigger point injection or other musculoskeletal service will be authorized outside VA. Authorization, referral requirements, timing, documentation, and cost responsibility can depend on the Veteran’s VA eligibility and the specific service requested. A non-VA practice cannot guarantee VA approval based on clinical need alone.
Commercial payer examples show variability
Commercial plans may use similar concepts but different thresholds. One policy may focus on focal muscle findings and conservative care history, while another may define repeat treatment rules differently or require prior authorization. Public commercial payer policies are examples only; employer group benefits, state rules, plan design, and updates can change how a specific claim is handled.
For example, Aetna’s public clinical policy material on back pain invasive procedures includes trigger point injection coverage language within a broader policy context, illustrating that commercial payers may define medical necessity and repeat-treatment expectations in their own way; patients can review the Aetna clinical policy bulletin as an example of payer-specific language. This does not mean Aetna covers every trigger point injection, and it does not determine coverage for BlueCross BlueShield, Cigna, Medicare, VA, or any individual plan.
Because the language is not uniform, it is risky to assume that a policy seen online applies to your plan, your employer group, or your specific benefits. Comparing your plan language with documented trigger point injection criteria can help guide questions, but it does not guarantee payment.
Joint Health Solutions provides insurance information to help patients understand that coverage varies. If you are considering an evaluation at the Charlotte clinic, you can also contact Joint Health Solutions or call 704-833-3566 with practical scheduling and coverage questions. This does not guarantee approval, coverage, or a specific outcome.
Repeat trigger point injections and why rules differ
Repeat trigger point injections usually receive more scrutiny than an initial injection because payers want to know whether the prior treatment was clinically useful and whether continued care is medically reasonable. Some policies may ask for documentation of pain relief, improved function, increased range of motion, or the ability to participate more effectively in conservative care. Others may set limits on sessions within a defined period.
Patients should treat any repeat-session limit found online as plan-specific until verified. A Medicare billing article from another jurisdiction, a commercial payer bulletin, or a summary from a third-party website may not apply to a Charlotte patient’s plan. The current policy version, jurisdiction, plan type, and individual benefits all matter. Written confirmation is especially helpful when repeat care, prior authorization, or appeal rights are involved.
The key point is that repeat trigger point injections are not usually approved simply because pain returns. The record may need to show that the diagnosis still fits, that prior care produced meaningful benefit, that conservative care remains part of the plan, and that another injection is reasonable under the payer’s policy. If a patient did not improve after a prior injection, the clinician may need to reconsider the diagnosis or treatment strategy.
Questions to ask before another injection
Before repeat care, patients can ask what must be documented for their plan, how response to prior treatment will be measured, and whether there are limits on the number of sessions. It may also be useful to ask how the injection supports function, movement, therapy participation, or daily activities. These questions keep the discussion focused on medical necessity instead of frequency alone.
It is also reasonable to ask whether symptoms still appear to come from myofascial trigger points. Pain patterns can change over time. Joint degeneration, tendon irritation, nerve involvement, bursitis, or other musculoskeletal conditions may become more prominent and may require a different care pathway. Updated trigger point injection criteria review can help keep repeat care from becoming automatic or disconnected from current findings.
Where trigger point injections fit in non-surgical care

Trigger point injections are one minimally invasive option that may be considered for assessed muscle knots or localized tension when appropriate. They are not the same as joint injections, cortisone injections, PRP therapy, hyaluronic acid injections, or IV therapy. Each treatment has different uses, criteria, evidence considerations, and coverage issues. A clinical assessment helps determine which, if any, option fits the patient’s symptoms.
At a conservative, non-surgical clinic, the care plan may include multiple components. For example, a patient with shoulder pain may have joint irritation, muscle guarding, and movement limitations. Another patient with knee arthritis may develop hip or back muscle tension because they are changing how they walk. In these situations, trigger point injection criteria focus on the specific muscle finding, not the entire pain condition.
That distinction can help patients avoid two common misunderstandings. First, having arthritis or joint pain does not automatically mean a trigger point injection is appropriate. Second, having a muscle knot does not mean injections are the only option. The decision depends on the assessment, the care plan, payer rules, and the patient’s goals.
Documentation patients can prepare before scheduling
Patients do not need to arrive with perfect paperwork, but organized information can make the visit more productive. If you are researching trigger point injection criteria before scheduling, consider writing down the location of pain, how long it has been present, what activities make it worse, what movements feel restricted, and what treatments you have already tried. Include dates or approximate timeframes when possible.
Conservative-care history can be especially helpful. If you completed physical therapy, followed a home exercise program, modified activity, used medications recommended by another clinician, or tried other non-invasive measures, bring that information. If a treatment was not tolerated or was not appropriate for you, tell the clinician rather than leaving a gap in the history.
Insurance-related documentation may also matter. Some plans require prior authorization or plan-specific medical necessity review. Others may ask for notes showing exam findings, functional limitation, and conservative care. Because trigger point injection coverage can vary, patients should not rely on general internet information as proof that a procedure will be covered.
Helpful details to share during the visit
- The most specific location of the pain or muscle knot.
- Whether pressing the spot reproduces your familiar pain.
- Whether the pain limits reaching, turning, walking, sleeping position, or exercise.
- What conservative therapy for muscle pain has already been tried.
- Whether previous injections or therapy helped, did not help, or had only temporary effects.
- Which insurance plan you want the practice and insurer to verify, if coverage is a concern.
These details do not determine candidacy by themselves. They simply support a clearer clinical assessment and help the care team understand whether documented trigger point injection criteria may be present.
When an evaluation at the Charlotte clinic may be useful
An evaluation may be useful when localized muscle pain, tightness, or a tender knot is interfering with movement and conservative measures have not been enough. It may also be useful when you are unsure whether symptoms are coming from a muscle trigger point, a joint condition, or another musculoskeletal source. Joint Health Solutions offers conservative, minimally invasive, non-surgical care at its north Charlotte clinic for adults with assessed joint pain and related musculoskeletal concerns.
The clinic is located at 9350 Benfield Rd, #109, Charlotte, NC 28269. Patients from nearby areas may travel to the Charlotte clinic, but Joint Health Solutions does not have physical branches outside Charlotte and does not provide mobile or in-home treatment. If symptoms are sudden, severe, or could represent an emergency, call 911 or seek emergency care instead of using a clinic appointment request.
If you want to discuss whether trigger point injections or another non-surgical option may fit your situation, you can schedule a consultation or call the Charlotte clinic at 704-833-3566. Suitability depends on clinical assessment, and results vary. The practice can help review covered and out-of-pocket costs before treatment, but no article or appointment request can guarantee insurance approval. Bring any plan documents or prior treatment notes that may help clarify trigger point injection criteria for your situation.
Practical takeaways for patients comparing options
Trigger point injection criteria usually come down to three linked questions: is there a clinically identifiable trigger point, has conservative care been addressed, and does the documentation support medical necessity under the patient’s plan? If the answer is unclear, the next step is not to assume the injection is wrong or right. The next step is an appropriate assessment and a careful review of benefits when coverage matters.
Patients should also remember that payer policies are administrative tools, not personalized medical advice. A policy may describe when trigger point injections are covered, but a clinician still needs to evaluate the individual patient. Similarly, a clinician may consider an injection appropriate, but a payer may still apply plan-specific coverage rules. Both issues matter before treatment.
For general education only; not a substitute for professional medical advice, diagnosis, or treatment. Suitability and results vary, and individual needs require clinical assessment.
Frequently Asked Questions
What is a trigger point injection?
A trigger point injection is an injection directed at an assessed muscle trigger point or localized muscle knot. It may be considered when exam findings support a myofascial pain source and the treatment fits the patient’s broader care plan.
What findings usually support trigger point injection criteria?
Commonly discussed findings include localized skeletal-muscle pain, a tender trigger point, a palpable taut band or nodule, restricted motion or functional limitation, and documentation that conservative care has been tried or considered when appropriate.
Does conservative care need to be tried first?
Many payer policies expect conservative care before trigger point injections unless it is not appropriate, not tolerated, contraindicated, or insufficient. The exact requirement varies by plan, so patients should verify their own coverage rules.
Do VA benefits automatically cover community care for trigger point injections?
No. VA community care generally requires VA eligibility and authorization. Veterans should work through VA channels to confirm whether outside care is approved for the specific service before scheduling.
Why do repeat trigger point injection rules vary?
Repeat treatment rules vary because each payer can define medical necessity, session limits, documentation requirements, and prior authorization differently. Some plans may require proof that earlier treatment improved pain, function, or participation in conservative care.
Are trigger point injections usually part of a broader plan?
Yes. Trigger point injections are commonly discussed as part of a broader treatment plan that may include physical therapy, home exercise, activity changes, or other conservative care. They are not usually treated as a stand-alone solution for every type of pain.
Does Medicare use the same rules as commercial insurance?
No. Medicare-related policies, Medicare Advantage rules, VA processes, and commercial insurance policies can differ. Patients should confirm current plan-specific requirements before treatment, especially when prior authorization, repeat care, or cost sharing is a concern.
What should I ask before scheduling?
Ask whether your symptoms appear consistent with myofascial trigger points, what conservative care should be documented, whether your plan has trigger point injection coverage criteria, and what covered or out-of-pocket costs should be reviewed before treatment.



 English
 Spanish