Shoulder Viscosupplementation in Charlotte: Hyaluronic Acid Injections for Shoulder Osteoarthritis
Published July 9, 2026 | Last reviewed: July 14, 2026 | Category: Joint Health, Non-Surgical Treatments | Location: Charlotte, NC
🕒 13 MIN READ
If shoulder pain is preventing you from reaching overhead, lifting your arm to fasten a seatbelt, or sleeping comfortably, osteoarthritis of the shoulder joint may be the cause. For patients with mild to moderate shoulder OA who have not found adequate relief from first-line care, viscosupplementation — injecting hyaluronic acid directly into the shoulder joint — is a non-surgical option worth understanding.
At Joint Health Solutions in Charlotte, we evaluate whether hyaluronic acid injections, alongside other non-surgical approaches, may be appropriate for each individual patient. This article explains what viscosupplementation is, what the evidence shows for the shoulder specifically, what the FDA status means, who may be a candidate, and what to expect.
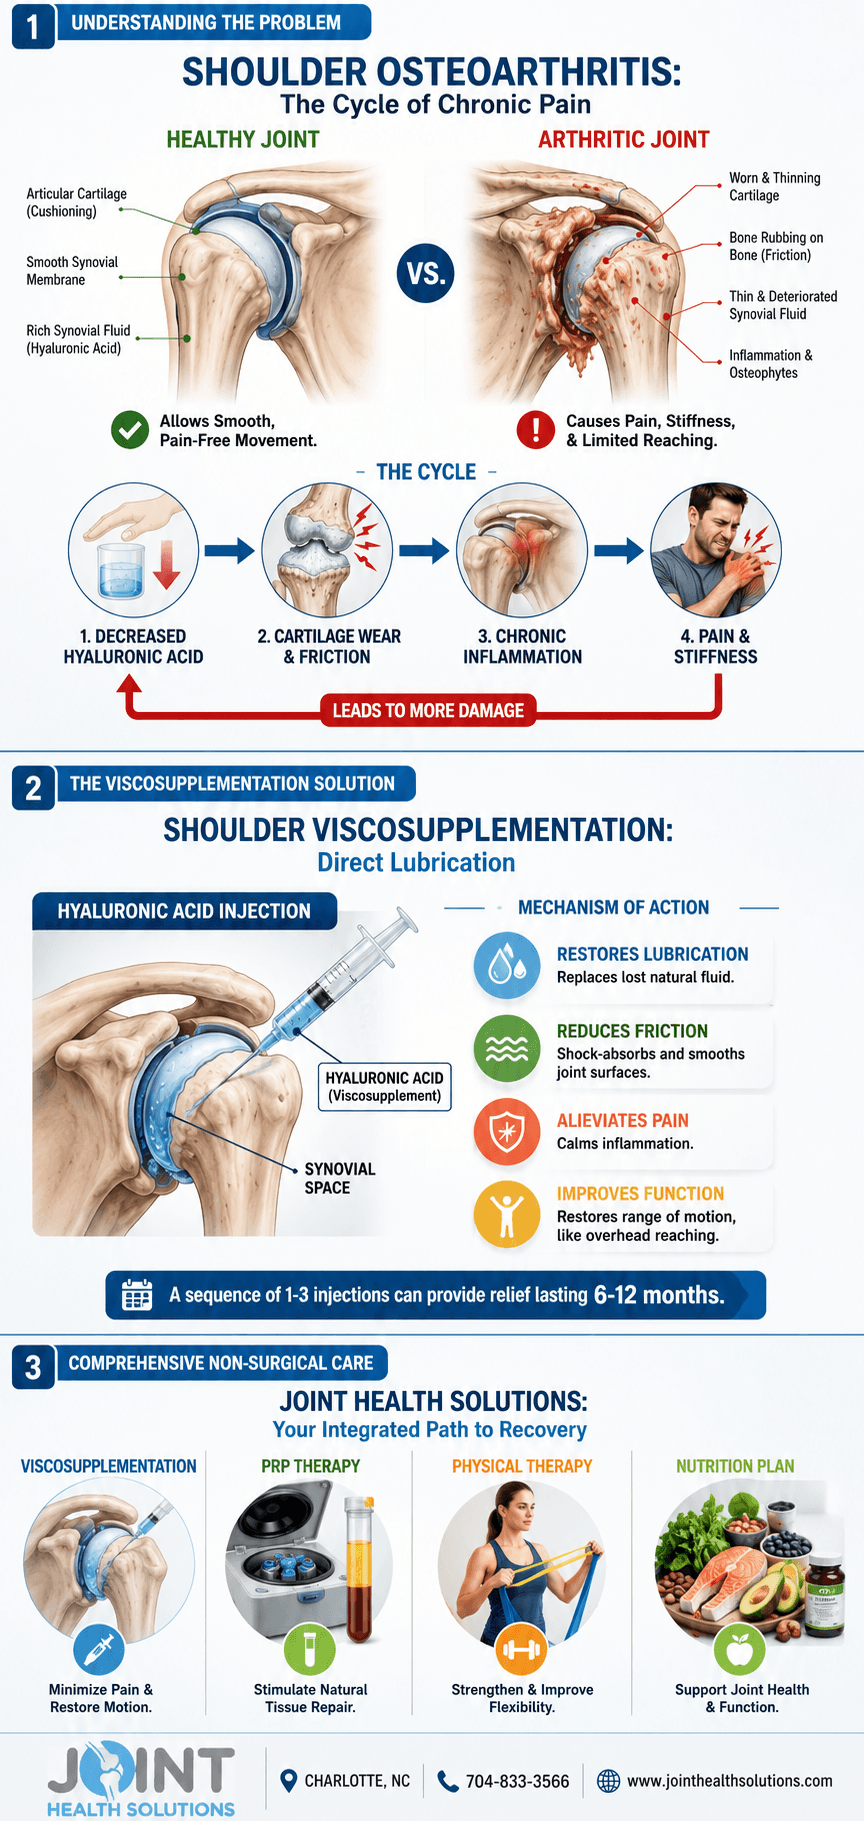
Viscosupplementation involves injecting hyaluronic acid — a naturally occurring component of healthy joint fluid — into the shoulder joint to supplement lubrication and reduce friction. In arthritic shoulders, the synovial fluid loses viscosity and protective quality, contributing to pain and stiffness. Hyaluronic acid injections aim to restore some of that lubricating function.
For knee osteoarthritis, several hyaluronic acid products are FDA-approved. For the shoulder, clinical evidence supports its use in selected patients, though most products are used off-label for this joint (see FDA status section below). A typical course involves one to three injections. Duration and degree of response vary considerably by patient; not all patients experience meaningful benefit. Candidates typically have mild to moderate shoulder OA confirmed by imaging and have not responded adequately to conservative treatments including physical therapy and NSAIDs. A clinical evaluation is required to determine whether this treatment is appropriate.
Why Shoulder Osteoarthritis Becomes Chronic: The Biology
The shoulder is a highly mobile ball-and-socket joint (the glenohumeral joint) where the head of the humerus articulates with the glenoid cavity of the scapula. In a healthy shoulder, articular cartilage covers the bone surfaces and synovial fluid — rich in hyaluronic acid — provides lubrication and cushioning.
As osteoarthritis develops, cartilage progressively thins and breaks down. The concentration and molecular weight of hyaluronic acid in the synovial fluid also decline, reducing the fluid’s viscous and elastic properties. This contributes to increased friction, inflammation, and pain. Because cartilage has limited capacity for self-repair, the degenerative process tends to progress without intervention.
Viscosupplementation aims to supplement the joint’s declining hyaluronic acid, potentially reducing friction and improving joint comfort in appropriate patients. It does not reverse cartilage loss or stop disease progression.
3 Common Causes of Shoulder Osteoarthritis
1. Age-Related Wear and Tear
The most common cause of shoulder OA is cumulative mechanical wear over decades. Cartilage naturally thins and loses resilience with age. This is most prevalent in adults over 50, though it can appear earlier in those with a history of heavy physical work or joint stress.
2. Previous Injury or Trauma (Post-Traumatic Arthritis)
A prior shoulder injury — dislocation, fracture, rotator cuff tear, or labral damage — can alter joint mechanics and accelerate cartilage wear, even years after the injury has healed. Post-traumatic arthritis is common in athletes and physically active adults.
3. Repetitive Overhead Activity
Occupations or sports requiring repetitive overhead movements (carpentry, painting, swimming, tennis, baseball) place sustained mechanical stress on the glenohumeral joint. Over time, this can deplete the joint’s protective structures and contribute to early-onset arthritis.
Symptoms That Suggest a Clinical Evaluation
- Deep, persistent aching pain in the shoulder, often worsening with overhead activity
- Stiffness that limits your ability to lift the arm or reach behind your back
- Grinding, clicking, or popping sensations (crepitus) during shoulder movement
- Localized swelling or tenderness around the joint capsule
- Night pain that disrupts sleep
- Progressive loss of range of motion
These symptoms can result from osteoarthritis, rotator cuff pathology, bursitis, or other conditions. A proper diagnosis — including physical examination and imaging — is necessary before any treatment is selected.
.
Understanding Your Treatment Options
Shoulder osteoarthritis is typically managed through a stepped approach. Each option has established benefits, known limitations, and appropriate patient populations.
Oral Medications (NSAIDs and Acetaminophen)
NSAIDs (ibuprofen, naproxen) and acetaminophen are guideline-recommended first-line options for OA pain with established evidence for symptom relief. They do not address the structural joint changes. Long-term NSAID use carries gastrointestinal, renal, and cardiovascular risks that should be monitored by a provider.
Corticosteroid Injections
Corticosteroid (steroid) injections have established evidence for short-term anti-inflammatory relief in shoulder OA and are useful for managing acute flares. They are not a long-term strategy — repeated injections over time may have adverse effects on cartilage and surrounding tissue. Used judiciously, they remain a legitimate and guideline-supported tool.
Physical Therapy
Strengthening the rotator cuff musculature and improving shoulder mechanics is foundational, guideline-recommended care for shoulder OA. Physical therapy may also help slow functional decline by improving stability and offloading the joint. It should be part of any comprehensive management plan.
Hyaluronic Acid Injections (Viscosupplementation)
Hyaluronic acid injections supplement the synovial fluid. For the shoulder, evidence suggests benefit in selected patients with mild to moderate OA who have not responded to conservative care. FDA approval status differs between knee and shoulder — see the evidence section below for detail.
PRP Therapy
PRP therapy delivers concentrated growth factors from the patient’s own blood to support tissue healing. Evidence for PRP in shoulder osteoarthritis is limited and mixed; it is not FDA-approved as a drug for this indication. It may be considered in selected patients who understand the evidence limitations.
Surgery
Total shoulder replacement is a well-established, effective option for patients with end-stage shoulder OA who have failed conservative care. Arthroscopy has a more limited role in shoulder OA compared to other conditions. Surgery carries standard risks and requires rehabilitation, but it should not be dismissed when clinically appropriate.
| Treatment | How It Works | Evidence Level | Key Limitations |
|---|---|---|---|
| NSAIDs / Acetaminophen | Reduce pain and inflammation | Established evidence for symptom relief | Does not address joint structure; systemic risks with long-term use |
| Corticosteroid Injections | Powerful local anti-inflammatory | Established evidence for short-term relief | Short duration; adverse effects with repeated use |
| Physical Therapy | Rotator cuff strengthening and mechanics | Established evidence; guideline-recommended | Requires adherence; may not fully resolve severe OA symptoms |
| Hyaluronic Acid Injections | Supplements synovial fluid | Clinical evidence in shoulder OA; off-label for most products | Results vary; not for advanced OA; FDA approval is knee-specific for most products |
| PRP Therapy | Growth factors to support tissue repair | Limited; mixed results in shoulder OA | Not FDA-approved for this indication |
| Surgery (Shoulder Replacement) | Replaces joint surfaces | Established for appropriate end-stage candidates | Invasive; recovery period; not for all patients |
FDA Status and Evidence for Shoulder Viscosupplementation
Several hyaluronic acid products (Synvisc, Euflexxa, Orthovisc, Gel-One, and others) are FDA-approved for knee osteoarthritis pain in patients who have not responded to conservative therapy.
For the shoulder, most of these same products are used off-label — meaning they are not specifically FDA-approved or FDA-cleared for shoulder OA as a drug indication. Some HA products may have broader 510(k) clearance as medical devices for joint injection, but this differs from a drug approval for a specific shoulder indication.
Off-label use is legal and common in medicine when supported by clinical evidence and physician judgment, but patients should understand the distinction. Joint Health Solutions should verify the specific product used and its regulatory status for the shoulder before publication of this article.
What the Clinical Evidence Shows
While the knee has the largest and most established evidence base for viscosupplementation, a growing body of studies addresses the shoulder specifically.
A 2012 systematic review by Merolla et al. published in the Musculoskeletal Surgery journal reviewed available trials and found that intra-articular HA injections reduced pain and improved function in patients with glenohumeral OA, with a generally favorable safety profile. A 2019 study by Brander et al. in the Journal of Shoulder and Elbow Surgery similarly reported improvements in pain and functional outcomes in shoulder OA patients who received HA injections compared to placebo, with effects sustained at six months in a subset of patients.
Overall, the shoulder evidence is less extensive than the knee evidence. Most studies are smaller, with shorter follow-up periods and variable preparation protocols. The level of benefit appears modest in many studies, and not all patients respond. These limitations should inform the clinical conversation before treatment.
| Component | FDA Status | Evidence Level | Key Findings |
|---|---|---|---|
| HA Injections — Knee OA | FDA-approved for knee OA pain (multiple products) | Established clinical evidence (multiple meta-analyses) | Modest pain relief and functional improvement; good safety profile; AAOS gives inconclusive recommendation reflecting mixed guideline views |
| HA Injections — Shoulder OA | Off-label for most products; product-specific — verify with manufacturer | Limited-to-moderate clinical evidence (smaller studies) | Some studies show pain reduction and improved shoulder function; evidence less extensive than for knee; not all patients respond |
| Chondroprotective Effects of HA | Not a separately approved FDA indication | Emerging / mechanistic evidence | Laboratory studies suggest HA may protect cartilage cells; clinical significance in humans not established |
Evidence-Level Definitions:
- FDA-approved: Product reviewed and approved by FDA for a specific drug indication.
- Off-label: Legal use of a product for an indication not specifically approved by FDA; common and appropriate when supported by clinical evidence and physician judgment.
- Established clinical evidence: Supported by multiple peer-reviewed human studies.
- Limited-to-moderate clinical evidence: Some human studies exist but are smaller or have shorter follow-up; benefit is plausible but less definitively established.
- Emerging / mechanistic: Early-stage research suggesting a mechanism; clinical relevance in humans not yet established.
How Joint Health Solutions Approaches Shoulder OA
We evaluate each patient individually to determine which combination of treatments best matches their clinical picture, imaging findings, prior treatment history, and goals.
Hyaluronic Acid Injections
When a patient is a candidate for shoulder viscosupplementation, we administer the injection directly into the glenohumeral joint. Fluoroscopic or ultrasound guidance is used to ensure accurate placement in the narrow joint space, which is more anatomically complex than the knee. A course typically involves one to three injections. We will discuss realistic expectations based on your OA grade and prior treatment response.
Learn more about our shoulder injections in Charlotte and our hyaluronic acid injection service.
Fluoroscopy-Guided Injections
The glenohumeral joint has a narrow space that can be difficult to access accurately by surface landmarks alone. Fluoroscopy-guided injection uses real-time imaging to confirm needle placement before the injection is delivered, improving accuracy and patient comfort.
Corticosteroid Injections
Cortisone injections are available when acute inflammation needs to be addressed before or alongside longer-term approaches. They are used judiciously, not as a standalone long-term strategy.
PRP Therapy
PRP therapy may be considered for concurrent rotator cuff tendinitis or other soft-tissue pathology alongside joint OA. For shoulder OA itself, PRP evidence is limited, and candidacy is assessed individually with a clear discussion of the evidence basis.
Physical Therapy
Physical therapy targeting the rotator cuff, periscapular muscles, and shoulder mechanics is foundational to any shoulder OA management plan. We coordinate with physical therapists to support long-term function alongside injection therapy.
Anti-Inflammatory IV Therapy
IV nutrient therapy is available at our clinic. For shoulder OA specifically, evidence that IV therapy reduces joint pain or alters disease course is limited. It is not considered a standard or first-line treatment for shoulder osteoarthritis and should not replace exercise, physical therapy, or other evidence-based care.
Nutrition Support
An anti-inflammatory dietary approach may support overall health and complement other treatments. Diet cannot reverse structural joint damage but may help manage systemic inflammation. Nutrition plans are offered as part of a comprehensive strategy, not as a standalone treatment for OA.
What to Expect at Your First Appointment
Your first visit begins with a thorough review of your shoulder pain history, prior treatments, imaging, and functional goals. We perform a physical examination assessing range of motion, stability, and pain patterns. If current imaging is not available or does not fully characterize the joint damage, we may recommend X-rays or MRI to assess cartilage loss, rule out rotator cuff pathology, and confirm candidacy.
If you are a candidate for shoulder viscosupplementation, we explain the procedure, its evidence basis, realistic outcomes, and potential side effects before proceeding. The injection is performed in-office using fluoroscopic guidance to ensure accurate placement. Most patients tolerate it well. Some experience mild soreness or stiffness at the injection site for one to two days. We recommend avoiding heavy overhead lifting or strenuous shoulder activity for 48 hours after each injection.
Follow-up is scheduled to assess your response. If the injection series does not produce meaningful improvement, we will discuss next steps clearly rather than defaulting to repeat treatment.
Who May Be a Candidate?
- Mild to moderate shoulder osteoarthritis confirmed on imaging (X-ray showing joint space narrowing; MRI if rotator cuff pathology is suspected)
- Inadequate relief from first-line conservative care: physical therapy, NSAIDs, activity modification
- No active joint infection
- No known allergy to hyaluronic acid products
- Not appropriate for or not yet ready for surgical evaluation
Patients with end-stage OA (bone-on-bone) typically respond less well to viscosupplementation. Surgical evaluation may be the more appropriate next step for those patients. A thorough clinical assessment is required before any recommendation.
Questions to Ask Before Starting Treatment
- Is the hyaluronic acid product you use FDA-approved for knee OA or specifically cleared for shoulder use?
- How will the injection be guided — fluoroscopy or ultrasound — and why?
- What realistic outcomes should I expect given my OA grade?
- How many injections will I need and how far apart?
- What is the plan if I do not respond?
- Is this covered by my insurance for the shoulder specifically?
- Can I combine this with physical therapy?
Frequently Asked Questions
Is shoulder viscosupplementation FDA-approved?
Most FDA-approved hyaluronic acid products are specifically approved for knee osteoarthritis. For the shoulder, use is typically off-label — meaning the product is not specifically approved for that joint as a drug indication, though the use is legal and supported by clinical evidence. Some products may have broader device clearances. Patients should ask their provider which specific product will be used and its regulatory status for the shoulder. Off-label use is common in medicine when evidence and clinical judgment support it.
How long does relief from shoulder viscosupplementation last?
Duration varies considerably. Some patients report improvement for several months; others experience shorter benefit or do not respond. The shoulder evidence base is smaller than the knee, and duration data varies across studies. Your provider will discuss realistic expectations based on your individual presentation before starting treatment.
Is the procedure painful?
Most patients tolerate it well. Fluoroscopic or ultrasound guidance improves injection accuracy in the shoulder’s narrow joint space. Some soreness, stiffness, or mild swelling at the injection site is normal for one to two days afterward. Serious complications such as infection are rare and will be discussed before the procedure.
How is a shoulder injection different from a knee injection?
The glenohumeral joint space is narrower and more anatomically complex than the knee joint, making accurate needle placement more technically demanding. Image guidance (fluoroscopy or ultrasound) is typically used for shoulder injections to confirm placement before the fluid is delivered. This improves both accuracy and patient comfort.
Can I combine viscosupplementation with physical therapy?
Yes, and we typically recommend it. Reducing pain through injection therapy may allow patients to participate more effectively in physical therapy, which addresses the muscle and mechanical factors that also contribute to shoulder dysfunction. The two approaches work better together for most patients.
How many injections will I need?
A standard course is one to three injections spaced approximately one week apart. The appropriate number depends on the product used and your provider’s clinical assessment. Your response to the first injection will help inform whether additional injections in the series are warranted.
Is this covered by insurance for the shoulder?
Coverage for shoulder viscosupplementation varies significantly by plan and is generally less consistent than for knee OA. Some plans cover it when prior conservative treatment is documented; others consider it investigational for the shoulder. Our team can verify your specific benefits before your appointment. Call us at 704-833-3566 to discuss.
Are there side effects?
Common side effects are mild and temporary: injection site pain, swelling, warmth, or redness lasting one to two days. A small subset of patients may experience a local inflammatory reaction (pseudoseptic reaction). Serious complications such as infection are rare. All risks are discussed before proceeding.
Can viscosupplementation be used if I have also had steroid injections?
Generally yes, but most providers recommend a washout period of several weeks after a corticosteroid injection before administering HA. Steroids can temporarily alter the local joint environment. Your provider will advise on appropriate timing based on your history.
Will this help me avoid shoulder replacement surgery?
For some patients with mild to moderate OA, non-surgical treatments including viscosupplementation may delay the progression of symptoms enough to postpone surgical evaluation. However, HA injections do not reverse joint damage. Patients with advanced OA may ultimately require shoulder replacement regardless of injection outcomes. The goal is to manage symptoms and maintain function through appropriate non-surgical care for as long as is practical.
What other shoulder conditions might be treated alongside OA?
Shoulder OA often coexists with rotator cuff tendinitis, bursitis, or partial cuff tears. These may be addressed with targeted physical therapy, corticosteroid injections, or PRP therapy depending on the clinical findings. A comprehensive evaluation allows us to address both the joint and the surrounding soft tissue when appropriate.
Schedule a Consultation in Charlotte
If shoulder pain is limiting your reach and daily activities, our board-certified providers at Joint Health Solutions can evaluate whether viscosupplementation or another non-surgical approach may be appropriate for your specific condition.
📞 Call us: 704-833-3566
What to bring to your first visit:
- Any prior shoulder imaging (X-ray films or reports, MRI reports)
- A list of current medications and supplements
- Notes on your symptoms — what movements trigger pain, what makes it better or worse
- Your insurance card and photo ID
- Questions for the provider about your diagnosis and treatment options
Sources
Institutional and Guideline Sources
- Mayo Clinic — Osteoarthritis: Diagnosis and Treatment
- Hospital for Special Surgery (HSS) — Viscosupplementation
- Arthritis Foundation — Osteoarthritis
Key Clinical References — Shoulder Viscosupplementation
- Merolla G, et al. (2012). Efficacy of hyaluronic acid injections for shoulder glenohumeral osteoarthritis: a systematic review and meta-analysis. Musculoskeletal Surgery. PubMed: 22661305
- Silverstein E, et al. (2007). Shoulder glenohumeral joint viscosupplementation: a prospective randomized trial. Journal of Shoulder and Elbow Surgery. PubMed: 17888684
- Colen S, et al. (2013). Hyaluronic acid injections in the glenohumeral joint: randomized double-blind trial comparing Hylan G-F 20 and the triamcinolone with triamcinolone alone. Journal of Shoulder and Elbow Surgery. PubMed: 22959524
- Altman RD, et al. (2015). The mechanism of action for hyaluronic acid treatment in the osteoarthritic joint: a systematic review. BMC Musculoskeletal Disorders. PubMed: 26578847
Disclaimer: This content is for informational purposes only and does not constitute medical advice. Always consult with a qualified healthcare provider to determine whether these treatments are appropriate for your specific condition. Individual results vary, and not every patient is a candidate. The FDA approval status of hyaluronic acid products for shoulder osteoarthritis differs from their approval status for knee osteoarthritis — patients should confirm the regulatory status of the specific product used with their provider. All medical claims, outcome statements, and product regulatory claims should be verified by Joint Health Solutions before publication.